
Which Medical Plan do I Choose?
Choosing the right medical plan is key because it affects both your care and your costs. Things to consider:
● How often you visit the doctor
● Your prescriptions
● What you can comfortably pay out-of-pocket for the unexpected.
Pick the plan that best fits your needs and budget to protect both your health and your wallet. We’ve got you covered!
This chart gives you a quick look at what each plan offers so you can find your best fit.
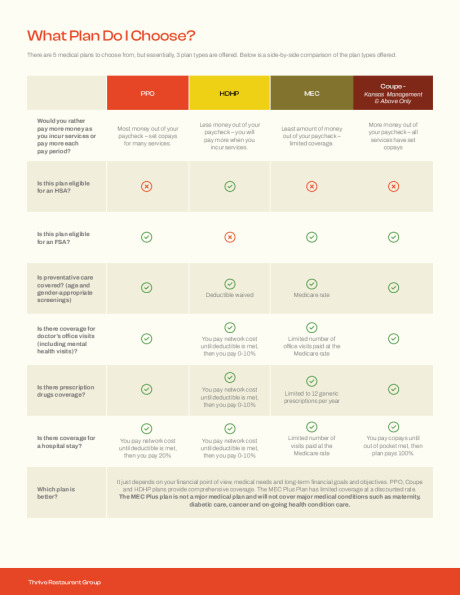
What Plan Do I Choose 2026
How to Stretch Your Healthcare Dollars
Major Medical Plans
At Thrive Restaurant Group, we believe your health is the foundation of your success. That’s why we’re proud to offer high-quality medical coverage to you and your family.
Below, you’ll find a quick overview of each plan so you can choose what fits your life best. For all the fine details, be sure to check the Summary Plan Descriptions (SPDs).
PPO & HDHP Plan
| Gold PPO | Silver HDHP | Bronze HDHP | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| In-Network | Out-of-Network | In-Network | Out-of-Network | In-Network | Out-of-Network | |||||||
| Annual Deductible (Re-starts January 1st) | ||||||||||||
| Individual / Family | $1,000 / $2,000 | $2,000 / $4,000 | $3,400 / $6,800 | $6,800 / $13,600 | $5,000 / $10,000 | $10,000 / $20,000 | ||||||
| Coinsurance | You pay 20% after the deductible | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Maximum Out-of-Pocket | ||||||||||||
| Individual / Family | $3,650 / $7,300 |
$7,300 / $14,600 |
$6,800 / $13,600 |
$13,600 / $27,200 |
$5,000 / $10,000 |
$10,000 / $20,000 |
||||||
| Physician Office Visit | ||||||||||||
| Primary Care | $30 copay | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Specialty Care | $50 copay | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Teladoc | $0 copay | You pay 40% after the deductible | $0 copay | $0 copay | $0 copay | $0 copay | ||||||
| Preventive Care | 100% deductible waived | You pay 40% after the deductible | 100% deductible waived | You pay 40% after the deductible | 100% deductible waived | You pay 40% after the deductible | ||||||
| Facility Services | ||||||||||||
| Urgent Care | $75 copay | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Emergency Room | $250 copay, subject to deductible & coinsurance | $250 copay, subject to deductible & coinsurance | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Complex Radiology (MRI, PET, CT Scans) | You pay 20% after the deductible | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Inpatient & Outpatient Facility | You pay 20% after the deductible | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Mental Health & Substance Abuse | ||||||||||||
| Inpatient | You pay 20% after the deductible | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Outpatient | $30 copay for office visits | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Prescription (No deductible applied) | ||||||||||||
| Generic | $10 copay | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Brand | $40 copay | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Brand (non-preferred) | $80 copay | You pay 40% after the deductible | You pay 10% after the deductible | You pay 40% after the deductible | You pay 0% after the deductible | You pay 40% after the deductible | ||||||
| Specialty Prescriptions | Not covered - Call Ventegra (877) 867-0943 for assistance | |||||||||||
Medical Plans Compared: HDHP vs PPO
Coupe Health (Kansas Managers & Above Store Leadership Only)
The Coupe Health plan makes healthcare simple—no deductibles, no co-insurance, no surprise bills. This plan has a set list of prices for care, so you always know what you’ll pay before you go. Check out the Coupe Health website to shop for providers in your area.
View this video to learn more about Coupe Health.
Need help or have questions? Coupe Health has a concierge team to help you navigate your health with confidence.
Call: 1-866-777-0624
| Coupe Health | Tier 1 | Tier 2 | Tier 3 | Out-of-Network* | ||||
|---|---|---|---|---|---|---|---|---|
| Annual Deductible (Re-starts January 1st) | ||||||||
| Individual / Family | $0 | |||||||
| Coinsurance | N/A | |||||||
| Maximum Out-of-Pocket | ||||||||
| Individual / Family | $3,650 / $7,300 | Unlimited | ||||||
| Service Description | Tier 1 | Tier 2 | Tier 3 | Out-of-Network* | ||||
| Preventive Care | 100% covered | 100% covered | 100% covered | 100% covered | ||||
| Primary Care | $20 | $25 | $40 | $50 | ||||
| Specialty Care | $35 | $50 | $80 | $100 | ||||
| First Stop Health | $0 copay | $0 copay | $0 copay | $0 copay | ||||
| Routine Labs | $20 | $25 | $40 | $50 | ||||
| Advance Labs | $60 | $80 | $130 | $155 | ||||
| Routine Radiology | $80 | $100 | $160 | $190 | ||||
| Complex Radiology (MRI, PET, CT Scans) | $230 | $310 | $520 | $630 | ||||
| Outpatient (PT, OT, ST) | $35 | $50 | $80 | $100 | ||||
| Urgent Care | $45 | |||||||
| Emergency Room / Ambulance | $200 / $200 | |||||||
| Outpatient Facility | $810 | $1,080 | $1,820 | $2,180 | ||||
| Complex Radiology (MRI, PET, CT Scans) | $230 | $310 | $520 | $630 | ||||
| Inpatient Facility | $2,000 | $2,600 | $4,400 | $5,280 | ||||
| Durable Medical Equipment | $115 | $155 | $160 | $320 | ||||
| Chiropractic Care / Accupunture | $35 | $50 | $80 | $100 | ||||
| Prescription | ||||||||
| Generic | $10 | $10 | $10 | 40% of cost | ||||
| Brand | $40 | $40 | $40 | 40% of cost | ||||
| Brand (non-preferred) | $80 | $80 | $80 | 40% of cost | ||||
| Specialty Prescriptions | Not covered - Call Ventegra (877) 867-0943 for assistance | |||||||
BCBS My Health Toolkit Flyer
Allied Benefit – Minimum Essential Coverage Care Plus Plan
This is not a major medical plan and will not cover all medical services. Below are some things to keep in mind:
1. This is a limited benefit plan and may not cover certain medical services. Certain covered services have a maximum allowed number of visits per year, per participant.
2. This plan does not utilize a provider network. Instead, doctors and hospitals are reimbursed based on pricing set by the federal government, known as the Medicare Fee Schedule.
3. Healthcare professionals have the right to decide whether or not to accept this amount for individuals covered under a non-Medicare health plan as payment in full. As a result, you may be subject to a balance bill.
Allied Benefit - MEC Care Plus+
| Allied Benefit - MEC CarePlus+ | ||||
|---|---|---|---|---|
| Non-Network | ||||
| Annual Deductible & Out-of-Pocket Max | ||||
| Individual / Family | N/A | |||
| Physician Office Visit | ||||
| Primary Care, Specialty Care or Mental Health | 100% of the Medicare Rate, limit to 6 office visits per plan year | |||
| X-ray and Lab Tests | 100% of the Medicare Rate, limit to 5 per plan year | |||
| First Stop Health | $0 copay | |||
| Chiropractic or Physical Therapy | Not covered | |||
| Preventive Care | ||||
| Adult Periodic Exams | 100% of the Medicare Rate | |||
| Well-Child Care | 100% of the Medicare Rate | |||
| Facility Services | ||||
| Complex Radiology (include MRI, PET or CT scans) | Not covered | |||
| Urgent Care or Emergency Room Facility | 100% of the Medicare Rate, limit 5 visits per plan year | |||
| Inpatient Facility | 100% of the Medicare Rate, limit 5 days per plan year | |||
| Outpatient | 100% of the Medicare Rate, limit 3 visits per plan year | |||
| Prescription | Retail Pharmacy (30 Day) | Mail Order (90 Day) | ||
| Generic (Tier 1) | $5 copay, limited to 12 prescriptions per plan year | Not covered | ||
| All other Rx | Not covered | Not covered | ||
Prescription Drug Benefit is administered by Caremark. Call (877) 860-6415 or visit www.caremark.com with questions.
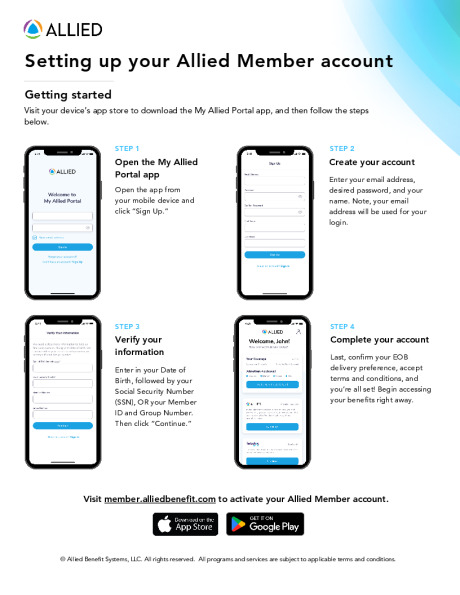
 English
 Español